Medical Device Manufacturing Insights & Blog
Industry updates, engineering leadership, and vertical integration strategies from MedTech contract manufacturing experts.
Why Choose Tracheostomy and Airway Tubes? This question requires more than a quick procedural answer. It demands careful assessment of breathing, airway protection, ventilation needs, and the patient’s long-term goals. Tracheostomy and Airway Tubes may support patients who need prolonged mechanical ventilation or have upper-airway obstruction. They can also make secretion management and bedside care more practical in selected cases.
Pulmonologist and tracheostomy researcher John F. Heffner, MD, has emphasized, “The decision to perform a tracheostomy should be individualized.” That principle remains essential. A tube can reduce airway resistance and improve access for suctioning. It may also support communication, rehabilitation, and gradual ventilator weaning when the clinical team selects the right design.
But a tracheostomy is not a simple shortcut. It creates a new care pathway. Nurses and caregivers must watch the skin, cuff pressure, secretions, tube position, and emergency equipment. A blocked tube can become dangerous within minutes. The patient may experience discomfort, altered speech, anxiety, or difficulty swallowing. These details are easy to underestimate.
Experience shows that outcomes depend on more than insertion technique. They also depend on training, follow-up, humidification, cleaning, and a clear emergency plan. The evidence is strong in some situations, yet uncertain in others. That uncertainty deserves honest discussion. Families should ask why the tube is needed, how long it may remain, and what successful recovery could look like. The best decision is individual, informed, and regularly reviewed.
What Tracheostomy and Airway Tubes Are
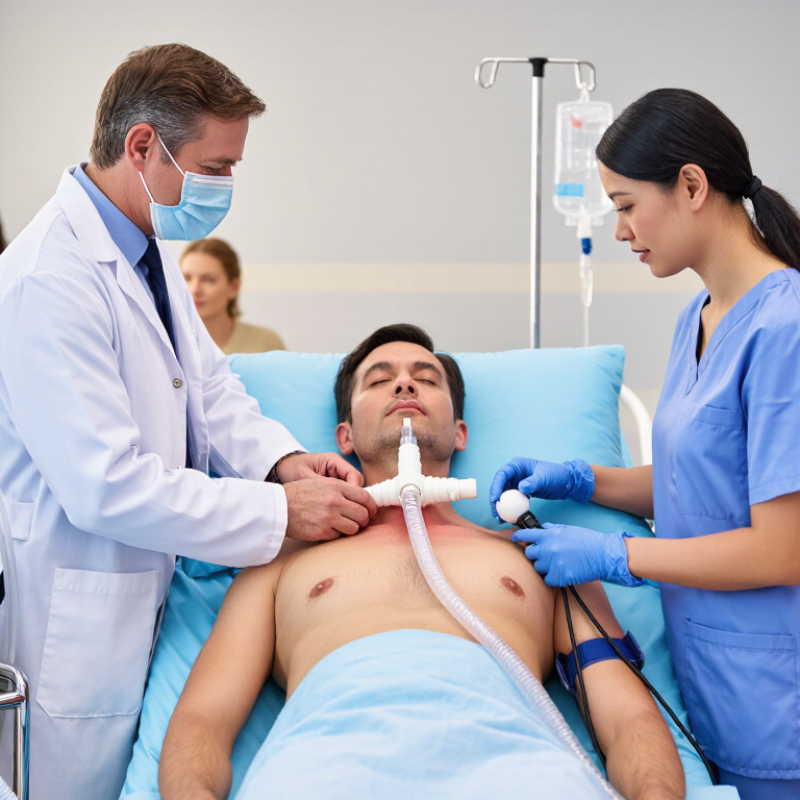
A tracheostomy is an opening made through the front of the neck into the windpipe, or trachea. A tracheostomy tube sits in this opening to help keep the airway accessible. It may support breathing, allow air to pass around an obstruction, or help clinicians manage airway secretions. The tube does not treat every cause of breathing difficulty. Its purpose depends on the person’s condition and care plan.
“Airway tube” is a broader term. It can refer to devices placed through the mouth or nose into the trachea, as well as tubes used through a tracheostomy opening. These devices differ in shape, placement, and function. Some have an inflatable cuff that helps direct airflow or limit leakage; others do not. Small details matter. A tube that fits one patient may be unsuitable for another.
Materials, size, and design are selected by qualified clinicians based on individual needs. Care can involve checking the tube’s position, keeping it clear, and watching the skin around the opening for irritation. This takes attention. Even a well-chosen tube can feel uncomfortable or require adjustment, and daily routines may take time to learn. Patients and caregivers should receive practical instruction from their healthcare team, since safe care varies with the tube and the person using it.
Why Choose Tracheostomy and Airway Tubes? - What Tracheostomy and Airway Tubes Are
Airway tubes are medical devices that help maintain or support airflow. The appropriate device depends on a person's airway, breathing needs, clinical condition, and expected duration of support. Selection and care should be guided by qualified healthcare professionals.
| Topic | Tracheostomy Tube | Other Common Airway Tubes |
|---|---|---|
| What it is | A curved tube placed through a surgically created opening (a tracheostomy) in the front of the neck into the trachea. | Examples include an endotracheal tube, passed through the mouth or nose into the trachea, and a supraglottic airway, positioned above the vocal cords. |
| Airflow route | Air enters and leaves through the neck opening. The route bypasses the nose and mouth and, in many cases, the upper airway. | An endotracheal tube passes through the mouth or nose and vocal cords. A supraglottic airway sits above the vocal cords and does not enter the trachea. |
| Typical clinical use | May provide a stable airway, support ventilation, or help manage airway obstruction or secretions. It may be considered when prolonged airway access is expected, depending on the patient's circumstances. | Endotracheal tubes are commonly used for airway protection or ventilation during emergencies, surgery, or critical illness. Supraglottic airways are commonly used for airway management during anesthesia or resuscitation in selected situations. |
| Cuff and airflow control | Some models have an inflatable cuff to help create a seal for ventilation; others are cuffless. A cuff does not eliminate all aspiration risk. | Many endotracheal tubes have an inflatable cuff for ventilation. Supraglottic airways use a seal around the upper airway; they do not provide the same airway protection as a cuffed tracheal tube. |
| Speech and airflow through the upper airway | Speech may be possible for some people with an appropriate tube, cuff status, and speaking valve, but this requires clinical assessment. A speaking valve should only be used when prescribed and safe for the individual. | An endotracheal tube passes through the vocal cords and generally prevents normal speech while in place. A supraglottic airway also occupies the mouth or throat and is typically used for temporary airway management. |
| Care considerations | Care may include keeping the opening and surrounding skin clean, managing humidification and secretions, checking the tube, and following a clinician-provided plan for suctioning and tube changes. | Care depends on the device and setting. Endotracheal and supraglottic airways require trained monitoring and management; they are not generally devices for unsupervised home use. |
| Potential risks | Possible complications include blockage by mucus, accidental displacement, bleeding, infection, skin irritation, and injury or narrowing of the airway. | Possible complications vary by device and include airway irritation or injury, misplaced or displaced tube, obstruction, and complications related to ventilation or aspiration. |
| How the device is selected | A healthcare team considers the reason for airway access, anatomy, breathing and secretion needs, ability to manage the tube, and whether the tracheostomy may later be removed. | The choice depends on the clinical situation, airway anatomy, urgency, procedure, and expected duration of support. Different airway devices are not interchangeable in every situation. |
This table is general educational information, not a diagnosis or treatment recommendation. A clinician should determine which airway device is appropriate and provide instructions for its use and care.
FAQS
It may be considered for prolonged ventilator support, an upper-airway blockage, or difficulty clearing secretions. The expected recovery and care goals also matter.
An endotracheal tube may support breathing during an emergency or surgery. A tracheostomy creates an airway through the neck.
No. Some people improve without one. The care team reviews progress, risks, alternatives, and personal preferences.
A cuffed tube has an inflatable balloon that can help manage airflow or leakage. An uncuffed tube has no balloon and is suitable only for some patients.
An inner cannula is a removable insert that can help with cleaning. Fenestrated tubes have openings that may direct air toward the upper airway.
Sometimes. A speaking valve may help with certain tubes, but a clinician must first confirm that airflow is safe.
They consider airway anatomy, breathing needs, ventilation, and care setting. A tube that is too large or too short may fit poorly.
Keep the skin clean and dry, follow instructions for cannula care, and use humidification or suction as taught. Check ties, too. Not too tight.
Seek urgent help for sudden breathing difficulty, blue lips, or a tube that cannot be cleared. Keep prescribed spare equipment nearby.
Written instructions, hands-on training, and scheduled reviews can help. Busy days happen; concerns should still be raised early.
Conclusion
Tracheostomy and Airway Tubes are medical devices that provide an alternative route for air to reach the lungs or help keep an airway open. A tracheostomy tube is placed through an opening in the neck into the windpipe, while other airway tubes may be used to support breathing or provide access for airway care. These devices may be considered when illness, injury, surgery, or a blockage makes normal breathing difficult or prolonged support necessary.
By maintaining access to the airway, these tubes can assist ventilation, help manage secretions, and support clinical care. Options vary in design, size, and features, and the appropriate choice depends on a person’s anatomy, breathing needs, expected duration of use, and care setting. Safe management includes regular assessment, cleaning and maintenance as directed by healthcare professionals, and monitoring for discomfort, blockage, or other complications. A care team can guide device selection and explain how to use and look after it.
